Two patients walk into the same office on the same day. The first has a CT scan showing a wide, open nasal airway and complains his nose feels permanently blocked. The second has a deviated septum visible from across the room and breathes fine. Neither presentation is rare. Both make sense once you understand something most people are never told about their own anatomy: your nose does not actually measure airflow. It infers it.
And the way it infers it can be tricked, dulled, or fooled in ways that affect how you feel every time you take a breath.
This is why a glass of mint tea can make your nose feel suddenly clearer without changing anything mechanical. It is why your nose feels stuffier on a dry winter morning even when nothing has changed since yesterday. And it is why some patients who have had a perfectly successful septoplasty still feel obstructed, while others with significant anatomical narrowing breathe just fine.
The science behind this is genuinely interesting, and it has practical implications for how patients understand their symptoms, how surgeons plan operations, and how we all should think about nasal health day-to-day.
The sensation of nasal patency is largely produced by cold-sensing receptors in the lining of your nose. When cool air evaporates a tiny amount of water from the mucosa, that cooling fires a receptor called TRPM8, and your brain reads the signal as "the nose is open and breathing." Anything that interferes with that cooling step, dryness, mucosal damage, warm humid air, will make your nose feel blocked even when nothing is mechanically obstructing it. Anything that activates the receptor directly, like menthol or eucalyptus, will make your nose feel open even when nothing has actually changed.
Otolaryngologists have known for decades that subjective and objective measures of nasal patency (the medical word for how open the airway is) often disagree. A patient can score severely obstructed on a symptom questionnaire and have a normal rhinomanometry result (rhinomanometry measures airflow and pressure inside the nose to calculate resistance). Another patient can score normal on the symptom questionnaire and have measurably high airway resistance.5 A 2017 review noted that subjective nasal patency correlates more strongly with mucosal temperature change than with airway resistance.8
This disconnect is not a small problem. Patient dissatisfaction rates after surgery for nasal obstruction have been reported as high as 30 percent, and long-term follow-up studies report higher failure over time.4 If the operation widens the airway and the patient still does not feel better, something is happening that the standard tools are not capturing.
What that something is, increasingly, looks like a problem of sensation rather than a problem of plumbing.
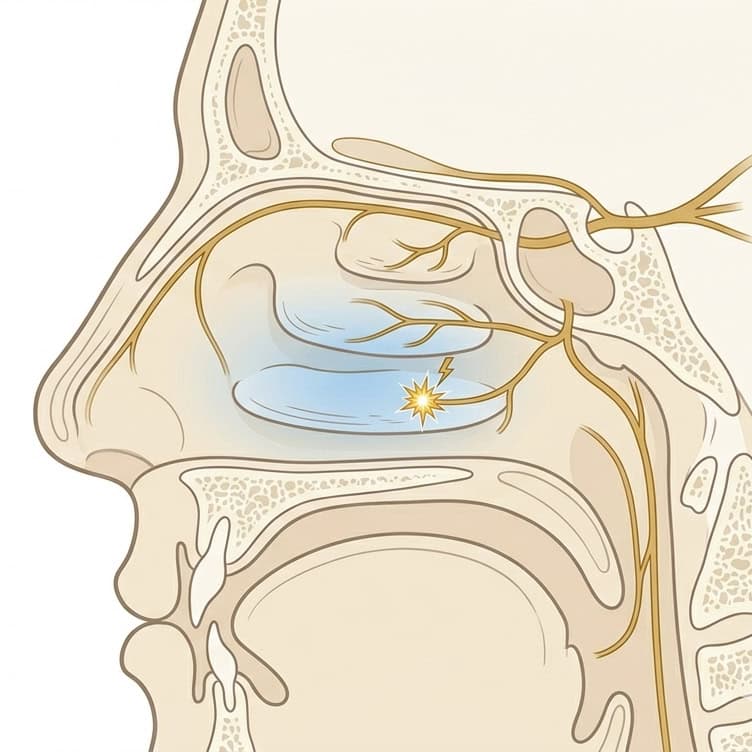
Most people picture their nose as a passive tube. Air comes in, air goes out, and somewhere along the way the brain checks whether the tube is open. But there is no mechanical sensor in the nose that measures airflow directly. There is no equivalent of a pressure gauge wired to your sense of breathing.
What your nose has instead is the trigeminal nerve, the same nerve that gives you the sting of an onion or the burn of horseradish. The trigeminal nerve carries dozens of different receptor types that respond to temperature, mechanical pressure, certain chemicals, and combinations of all three. The brain takes the signals from these receptors and assembles them into the feeling of "breathing through my nose."5,8
This means your sensation of airflow is, biologically speaking, a calculated guess. The receptors are sampling the conditions in your nose and the brain is inferring what must be happening with the air. Most of the time this guess is accurate. When the conditions get unusual, the guess can be very wrong.

The single most important player in nasal airflow sensation is a receptor called TRPM8. The name is unwieldy, but the concept is simple: it is a cold-sensing channel embedded in nerve endings throughout the nasal lining.
Recent research has shown that TRPM8 is expressed by more than 60 percent of trigeminal afferent fibres (the nerve fibres that carry signals from the body back to the brain) in the nasal mucosa.5 When the temperature of the mucosa drops below a certain threshold, the receptor opens, the nerve fires, and the brain receives a signal that translates roughly to "cool air is moving across the lining." The brain interprets that signal as a patent, open nasal airway.
The reason cool air activates this receptor is not obvious. It is not the temperature of the inhaled air itself, exactly. It is what happens when that air contacts wet mucosa. Cool, dry inhaled air pulls a small amount of water out of the lining by evaporation. Evaporation cools the surface it leaves, the same way sweat cools your skin. That local cooling drops the mucosal temperature by a degree or two, just enough to fire TRPM8. The brain reads the firing pattern as breath.
This mechanism is now supported by physical temperature measurements inside the nose, which show an inverse relationship between mucosal temperature and the perceived sensation of nasal patency, lower mucosal temperature, better-perceived breathing.5 Computational fluid dynamics studies (computer simulations of nasal airflow) have shown the same pattern: regions of peak mucosal cooling correlate with patient-reported scores on validated obstruction questionnaires.5,8
Now the explanation for the dryness experience falls into place.
If your mucosa is already dehydrated, there is less surface water available to evaporate. Less evaporation means less cooling. Less cooling means TRPM8 fires less. The brain receives a quieter signal, interprets it as reduced airflow, and produces the sensation of stuffiness, even though the geometry of the airway has not changed.
This is the same airway you had an hour ago. The same septum. The same turbinates (the curved, shelf-like structures along the side walls of each nostril that warm, humidify, and direct airflow). The only thing that changed is the moisture content of the lining and the firing rate of the receptors that report on it.
Several common scenarios produce exactly this pattern:

This is where the science gets fun, and where one of the most cited papers in this whole topic comes in.
In 1983, three researchers at University College Cardiff, Burrow, Eccles, and Jones, ran a clean experiment.1 They took 31 healthy volunteers and exposed each one to five minutes of menthol vapour, eucalyptus vapour, or camphor vapour, and measured nasal resistance to airflow before and after each exposure using rhinomanometry. They also asked each subject to rate, on a questionnaire, whether their nose felt cooler, and whether airflow felt improved.
The result was a perfect demonstration of the disconnect between objective and subjective.
Then the researchers did something clever. They had the same subjects exercise on a stationary bike for five minutes. Exercise causes genuine, measurable nasal decongestion through autonomic vasoconstriction (automatic narrowing of the small blood vessels in the turbinates), an effect every athlete has felt. Sure enough, nasal resistance dropped significantly after exercise. But here is the twist: very few subjects reported any cooling sensation or any improved sensation of airflow after exercising.1
So menthol gave people the feeling of a clear nose without changing the airway at all, while exercise gave them an actually clearer airway without much sensation of change. The two effects had been completely separated in the laboratory. The same group later confirmed the menthol-specific finding in a separate study using rhinomanometry alone.2
The same finding has been confirmed in patients with the common cold. A 1990 study gave 62 cold sufferers either an 11 mg menthol lozenge or a candy placebo, and measured both objective nasal resistance and subjective ratings of airflow.3 The menthol lozenge produced a significant improvement in subjective airflow within 10 minutes, while objective nasal resistance was unchanged. The placebo group reported nothing.
This is why Halls feel like they open your nose. Why Vicks VapoRub feels like it clears congestion. Why eucalyptus oil in a steam bowl feels so much like a decongestant. None of these things are decongestants in the pharmacological sense. They do not shrink swollen turbinates. They do not change nasal resistance. They directly activate TRPM8 receptors in the nasal mucosa, fire the cold-sensing nerve fibres, and tell your brain that air is moving freely through a cool, open nose. The sensation is real. The decongestion is not.
Menthol and related cooling compounds do not open your nose. They tell your brain your nose is open. For most everyday discomfort that distinction does not matter, the relief is genuine. But it is worth knowing if you ever wonder why a menthol product feels effective on a stuffy nose that an actual decongestant medication is not touching.
The most striking, and unfortunate, demonstration that nasal sensation depends on receptors and not on plumbing is a condition called empty nose syndrome (ENS).
ENS describes patients who, usually after aggressive turbinate surgery, develop a debilitating sensation of suffocation despite having a wide-open nasal airway. The CT scan looks excellent. The cross-sectional area is huge. Air moves through the nose without any measurable resistance. And yet the patient feels like they are unable to breathe, sometimes severely enough that the condition is associated with significant psychological distress.
For years this was considered a mysterious or even psychiatric problem. The current evidence points elsewhere. ENS patients have been shown to have reduced trigeminal sensitivity in the nasal mucosa and lower expression of the relevant receptors compared to healthy controls.4 The aggressive turbinate reduction did not just remove tissue. It removed the sensing surface that tells the brain breathing is happening. The airway is open. The receptors are gone. The brain reads silence and translates it as suffocation.
This is why most modern facial plastic and ENT surgeons take a strongly conservative approach to turbinates. Preserving mucosa is not just about humidification or filtering. It is about preserving the ability to feel your own breathing. As a 2009 review of the impact of nasal surgery on air-conditioning function put it, too much widening of the nasal cavity must be avoided.9
Septal deviation is the textbook explanation for nasal obstruction, and in many patients it is genuinely the cause. But septal deviation also reshapes airflow patterns inside the nose, which means it changes which areas of mucosa get cooled and which do not. Some patients with apparently severe deviations feel fine because the cooling pattern still falls in the right places. Others with mild deviations feel completely blocked because the cooling pattern is disrupted.
Recent work using calibrated air puffs to map trigeminal sensitivity has shown that the inferior turbinate is one of the key sites where mucosal sensitivity correlates with the perception of patency.4 The nasal vestibule is the most sensitive area to mechanical airflow stimuli, but the inferior turbinate is where subjective patency seems to be decided. This is consistent with computational fluid dynamics work showing that turbinate mucosa is where most of the heat loss, and therefore most of the TRPM8 activation, happens during normal breathing.5
What does this mean for surgical planning?
Areas of true mechanical narrowing: a deviated septum impacting the valve area, severely hypertrophied turbinates, or collapsed nasal valves (the narrowest part of the airway, just inside the nostril, where most of the resistance to breathing is generated). These are anatomical problems that respond to anatomical solutions.
Mucosa, specifically the lining of the inferior and middle turbinates and the anterior nasal cavity. This is sensing tissue. Removing too much of it produces a wide airway that does not feel like an airway.
Functional nasal surgery done well, septoplasty with carefully measured turbinate reduction rather than aggressive resection, has been shown to improve nasal heating and humidification rather than impair it.10 The right operation done the right way produces an airway that both works mechanically and feels right neurologically. The wrong operation, or the right operation taken too far, can do the opposite.
One last piece of the puzzle is harder to talk about but worth being honest about. Mental health affects how you perceive your nose.
A 2017 study of 495 patients presenting for rhinoplasty assessment found that patients with poor mental well-being and low self-esteem rated their nasal obstruction as significantly worse than mentally healthy patients with the same nasal airflow on objective testing.6 The objective measures (peak nasal inspiratory flow, airway resistance, minimum cross-sectional area) were clinically similar between groups. The subjective experience was not.
This is not a suggestion that nasal obstruction is "all in your head." It is a reminder that perception is built by a brain, and that brain is affected by mood, anxiety, and self-image. The same mucosal cooling produces a different experience depending on the state of the person feeling it. This finding has practical implications: a patient in real distress about their nose may benefit from objective airflow testing to clarify what is actually happening, and sometimes from supportive care alongside the surgical conversation.
The wider point is that nasal sensation is not a reliable readout of nasal anatomy. It is a constructed experience, and many things go into the construction.
Once you understand the cooling mechanism, the list of things that genuinely help, and the things that only feel like they help, becomes much clearer.
Saline irrigation. Rinsing the nasal cavity with isotonic or slightly hypertonic saline (salt water at the same or slightly higher concentration than your body fluids) does several useful things at once: it clears debris and crusts, hydrates the mucosa so evaporative cooling can work properly, and reduces inflammation. For most patients with a chronically stuffy-feeling nose, this is the highest-yield intervention there is.
Humidification. Especially in winter, especially in Ottawa, especially in homes with forced-air heating. A bedroom humidifier that keeps relative humidity around 40 percent overnight prevents the morning-stuffiness pattern. The goal is to keep the mucosa wet enough that evaporative cooling continues to work.
Hydration. Systemic, the boring kind. Drink water. The lining of your nose is downstream of your overall hydration status.
Treating actual inflammation. If allergic rhinitis or chronic rhinosinusitis is contributing to mucosal swelling, intranasal corticosteroids genuinely shrink the inflamed tissue and improve airflow. They take weeks to reach full effect but they work.
Topical menthol products. They produce a real subjective improvement and most people enjoy them. They do not actually decongest. This is fine for everyday discomfort. It is a problem if it leads someone to ignore an obstruction that needs proper assessment.
Hand-held fans aimed at the face. Interestingly, this does work, and not for the reason you might guess. The cooling sensation on the trigeminal-innervated skin of the face appears to reduce the perception of breathlessness through a similar receptor mechanism. There is reasonable evidence supporting hand-held fans as a first-line option for patients with chronic refractory breathlessness in palliative care settings.7 The same principle is why people experiencing a panic attack often feel better near an open window.
Decongestant nasal sprays. Products containing oxymetazoline or xylometazoline (Otrivin, Dristan, Drixoral) genuinely shrink turbinates and open the airway. They also produce rebound congestion if used for more than three to five days in a row, a condition called rhinitis medicamentosa. Patients who reach for the spray daily often end up with a nose that feels chronically blocked because of the spray itself. If you are using one of these every day, talk to your doctor about a tapering plan.
Most everyday nasal stuffiness is sensational, mucosal, and self-resolving. It does not need surgery. It needs saline, humidification, time, and patience.
It is worth seeing a physician if:
An assessment for nasal obstruction should not just be a look up the nose. A good evaluation includes a careful history (when does it feel worse, what triggers it), a structural exam (nasal valve, septum, turbinates, mucosa), often endoscopy (a thin, lighted scope passed gently through the nostril to see the deeper structures), and ideally objective airflow testing alongside a validated symptom score like the NOSE (Nasal Obstruction Symptom Evaluation) questionnaire or SCHONZ. The combination of objective and subjective measures is what catches the disconnect this whole article is about.
Your nose is not a tube with a sensor. It is a sensing surface, and the brain assembles the experience of breathing from a hundred quiet signals coming off that surface. Most of the time the signals match the airway. Sometimes they do not, and when they do not, the gap is where confusion happens.
If your nose feels stuffy in the morning and clears as the day goes on, you are probably experiencing dryness, not obstruction. If a Halls makes your nose feel suddenly clear, you are activating a cold receptor, not opening anything mechanical. If you have had a successful operation and still feel obstructed, the airway and the sensation are running on different tracks. And if your CT is clear but your nose feels closed, the problem is not in the bone or cartilage. It is in the lining and the receptors that live in it.
Knowing this does not solve the problem on its own. But it does change the questions a patient brings to a consultation, and it changes what good treatment should look like. The best operations preserve sensing tissue. The best non-surgical treatment supports the sensing tissue you have. And the most useful conversation about a stuffy nose starts not with "how blocked is it" but with "what is your nose actually telling your brain right now, and is the message getting through."
ARIA, our AI Rhinoplasty Information Assistant, is available around the clock to answer questions about nasal function, breathing, and what to expect from a consultation. She is trained on the same research cited on this page.
Ask ARIA NowARIA provides general information only. She is not a replacement for medical advice from Dr. Bonaparte.
Want to learn more? Read about deviated septum and other nasal conditions or explore our full rhinoplasty and nasal surgery blog.

A proper assessment of nasal obstruction looks at structure, mucosa, and sensation together. Dr. Bonaparte combines clinical examination with objective airflow testing to identify what is actually driving your symptoms.
Book Your Consultation